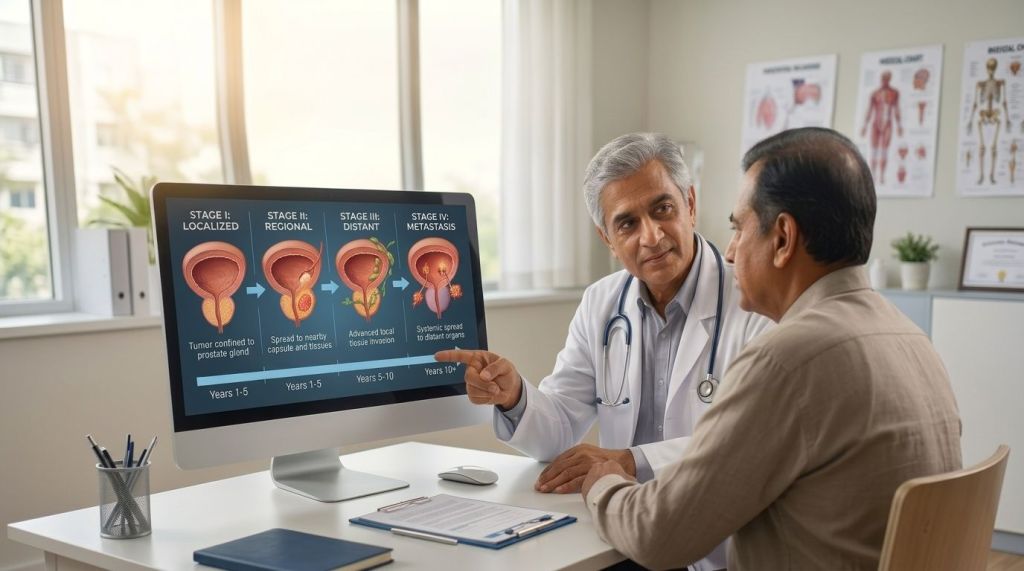
A prostate cancer diagnosis does not always mean that the cancer will immediately spread or cause serious symptoms. Some prostate cancers grow slowly and may remain confined to the prostate for years, while others can become aggressive and spread to different parts of the body.
Understanding how prostate cancer progresses over time can make PSA tests, scans and treatment decisions easier to follow. The course differs for everyone, so doctors consider several factors rather than relying on a single test.
Key Takeaways
- Prostate cancer may remain confined to the prostate or progress to nearby tissues, lymph nodes and distant organs.
- PSA, Grade Group, staging and imaging help doctors monitor how the disease is behaving.
- Metastatic prostate cancer can initially respond to hormone-based treatment but may eventually become castration-resistant.
- Regular follow-up helps doctors identify changes in the disease and adjust treatment when needed.
Prostate cancer can change gradually
Prostate cancer begins when abnormal cells grow in the prostate gland. At first, the cancer may remain within the prostate. This is called localised prostate cancer.
Doctors assess the extent and behaviour of the cancer using factors such as the TNM stage, Grade Group and PSA level. Staging shows whether the cancer is limited to the prostate, has reached nearby tissues or has spread to different parts of the body. The Grade Group describes how abnormal the cancer cells look under a microscope and indicates how aggressively they may behave.
From localised to locally advanced disease
When prostate cancer remains within the prostate, treatment depends on its risk category and the person’s overall health. Options can include active surveillance, surgery or radiotherapy.
Cancer that grows beyond the prostate into nearby tissues is considered locally advanced. It may involve structures such as the seminal vesicles or nearby lymph nodes. Treatment can involve a combination of local and hormone-based approaches, depending on how far the cancer has spread and its risk of recurrence.
This is why regular follow-up matters. A change in PSA or imaging findings may prompt doctors to reassess the disease and consider whether treatment needs to change.
PSA provides an important picture of disease activity
PSA, or prostate-specific antigen, is a protein produced by prostate cells. A blood test can measure its level and is an important part of prostate cancer monitoring.
After treatment with surgery or radiotherapy, a confirmed rise in PSA can indicate that the cancer may have returned. The speed of the increase can also provide useful information. PSA doubling time refers to how quickly PSA levels double, and a shorter doubling time is generally associated with a higher risk of progression in certain settings.
However, PSA is only one part of the picture. The EAU guidelines note that prostate cancer can sometimes progress on imaging without a corresponding PSA rise. This is especially important for men receiving treatment for advanced disease.
Cancer can eventually spread beyond the prostate
When prostate cancer spreads to different parts of the body, it’s called metastatic prostate cancer. The bones and distant lymph nodes are common sites of spread. Cancer that has spread to the bone is still prostate cancer, rather than bone cancer.
At this stage, treatment generally focuses on controlling the disease, slowing its growth and managing symptoms. Androgen deprivation therapy (ADT) lowers testosterone because many prostate cancer cells depend on androgens, or male hormones, to grow.
For metastatic hormone-sensitive prostate cancer, treatment is now commonly intensified by combining ADT with another systemic treatment rather than using ADT alone. The specific approach depends on the person’s disease, previous treatment and overall health.
Hormone resistance can develop over time
One of the major changes that may occur during prostate cancer progression is the development of castration-resistant prostate cancer.
This means the cancer continues to grow despite testosterone being reduced to very low levels. The cancer is not truly independent of hormones. Instead, cancer cells can adapt and continue using androgen-related pathways even when testosterone levels are low.
Progression can be identified through a rising PSA, new findings on scans or worsening clinical symptoms. Doctors also check testosterone levels because castration-resistant prostate cancer is defined by disease progression despite low levels of testosterone.
Treatment may change as the cancer changes
As prostate cancer progresses, treatment can be adjusted to target the ways cancer cells continue to grow.
Abiraterone acetate is one medicine used in specific settings of advanced prostate cancer. It blocks CYP17, an enzyme involved in androgen production. This reduces androgen production from the testes, adrenal glands and prostate tumour tissue. It is used with a corticosteroid in appropriate patients.
A medicine containing abiraterone acetate, such as Xbira 250 mg, may be prescribed as part of a doctor’s treatment plan. The dose and combination depend on the individual’s condition and should not be changed without medical advice.
This treatment also requires monitoring. Liver function is particularly important because liver abnormalities can occur, especially during the earlier months of treatment.
Monitoring remains important throughout treatment
Symptoms alone cannot always determine progression. Follow-up may include PSA testing, testosterone measurements, clinical assessment and imaging.
Depending on the situation, doctors may use CT, MRI, bone scans or PSMA-PET/CT to look for changes. For men with metastatic disease, the EAU recommends regular follow-up with imaging at intervals based on the disease and treatment.
This monitoring becomes especially important when PSA and scan results do not tell the same story. A stable PSA does not always mean that metastatic prostate cancer is completely stable, which is why doctors consider symptoms, blood tests and imaging together.
Conclusion
There is no single schedule that prostate cancer follows as it progresses. One person may have localised, slow-growing disease for many years, while another may develop recurrent or metastatic disease sooner.
The stage, Grade Group, PSA pattern, response to treatment and hormone sensitivity all help doctors understand where the cancer stands. Treatment can then be adjusted as the disease changes.
For patients and families, this can make the journey feel less predictable. Regular follow-up helps track those changes and supports treatment decisions based on what is happening at that time.
Disclaimer: This article is for general informational purposes only and should not replace advice from a qualified healthcare professional.


Leave a comment